Click on each panel below to link to HUNDREDS of in-language resources to share with your patients.

Click on each panel below to link to HUNDREDS of in-language resources to share with your patients.
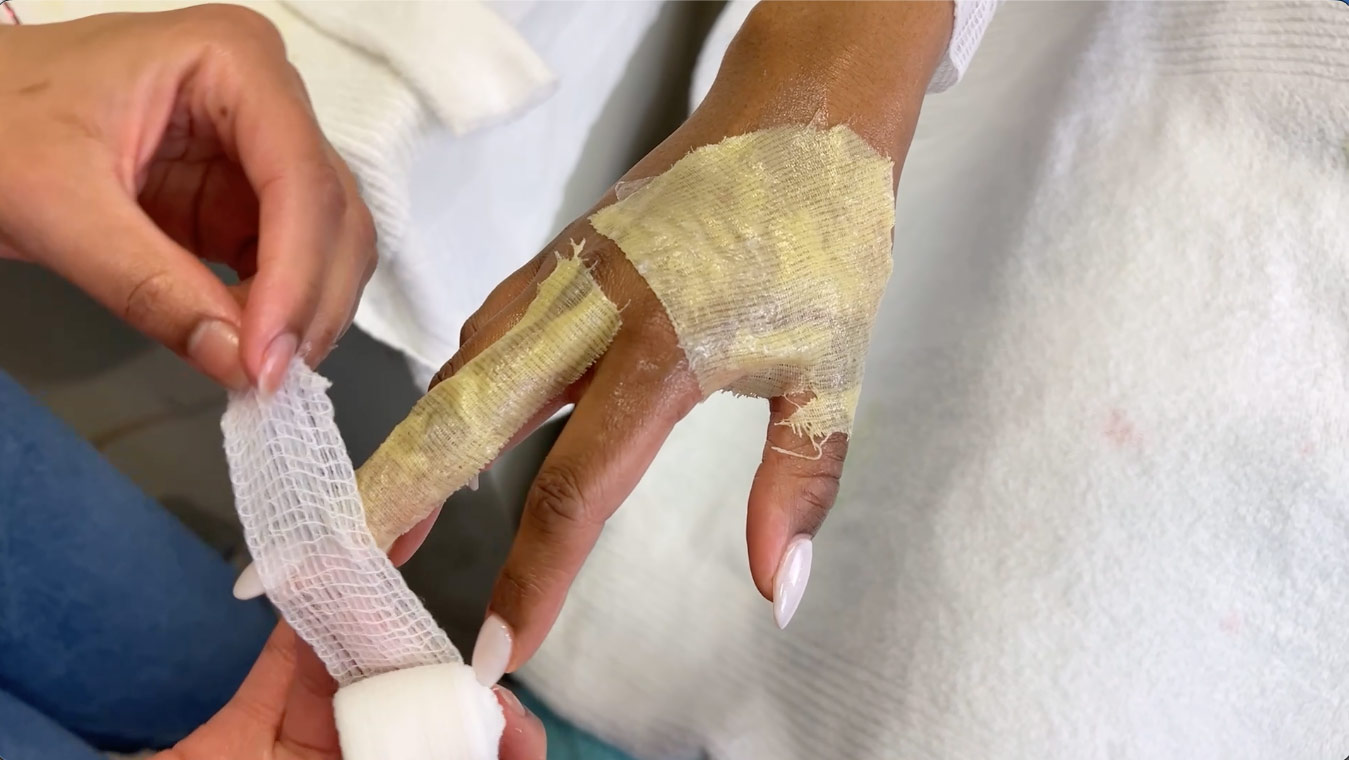
This instructional video provides step-by-step guidance for burn wound care using greasy gauze (Vaseline gauze) and standard gauze dressings. Designed for patients and caregivers, the video reinforces clinical instructions to be able to treat small burns at home, or to continue treatment for larger burns after seeing a healthcare provider.
In this video, you will learn:
This educational resource is intended to supplement the instructions provided by your medical care team. Always follow the guidance of your burn care provider. Printable PDF with QR Code with links to each video.
To improve accessibility and health equity, these burn care videos are being translated into multiple languages. Additional language versions will be added as they become available.
We encourage you to share these resources with your communities to support safe, informed burn recovery at home.
Suggested use for providers:
Burn care can be complex, involving multiple steps that may feel overwhelming for patients and caregivers. This challenge is even greater for individuals with Limited English Proficiency (LEP), who may face additional barriers in understanding and following detailed wound care protocols. As patients transition from hospital care to at-home recovery, it is essential that they clearly understand and follow proper burn wound care instructions to achieve the best possible outcomes. To address this need, EthnoMed partnered with Harborview’s Burns, Plastics, and Pediatric Acute Care Unit to develop accessible, visual education tools to support safe and effective burn care at home.
A burn is an injury to the skin caused by something hot, like fire, hot water, steam, or even touching something like a hot pan. Burns can also be caused by cold, electricity, chemicals, or the sun. No matter what causes the burn, the skin needs the right care to heal well and stay healthy.
A burn is an injury to the skin caused by something hot, like fire, hot water, steam, or even touching something like a hot pan. Burns can also be caused by cold, electricity, chemicals, or the sun. No matter what causes the burn, the skin needs the right care to heal well and stay healthy.
The Tuberculosis, TB Cultural Profile series on EthnoMed is a resource intended for medical providers who test, treat, or counsel patients about TB. These profiles aim to cover some of the main immigrant populations in the greater King County area in Washington state. However, they should be generally applicable to providers working in other areas of the United States.
TB disease cases continue to be present in the U.S. with an incidence rate of about 2.5 per 100,000 (WHO 2023). In King County, the rate is about double that of the U.S. (2023 TB Program Summary (kingcounty.gov)). The majority of TB disease cases in King County occur in patients born outside the U.S. and represent reactivation of remote latent TB infection (LTBI).
In collaboration with the Public Health Seattle & King County TB Program, we have become aware of barriers to TB testing and treatment, particularly amongst immigrant populations. Multiple factors contribute to screening and treatment hesitancy across these communities, including incomplete understanding of testing and treatment options for TB disease and LTBI, stigma, other disease associations, language barriers, and difficulties accessing the health system in the U.S.
This project has been generously supported by the following funders:
TB Elimination Alliance (2023-2024 Mini-Grant Program)
Firland Foundation (2024-2025 Community Grant)
Here, we provide a resource with profiles for some of the largest immigrant communities in the greater King County region. Outlines of these profiles and definitions of terms are provided below.
The outline of the TB Cultural Profiles follows the format below. Additional information contained in each section of the profiles is provided below this outline:
Provides essential points from the entire profile.
List of recommendations for screening, treating, and counseling for TB in the community.
Profiles are developed using a combination of semi-structured interviews with community members as well as a literature review. The number of community members interviewed and language used are provided here.
Listing of most recent TB statistics from the country discussed. These are typically obtained from the World Health Organization (WHO).
Lists of official and popular languages used and common terms for TB.
Rates of BCG vaccination and the year the vaccination was introduced in each country is obtained from www.bcgatlas.org. This section also includes community perceptions regarding BCG vaccination.
Narrative of responses from community interviews regarding symptoms recognized by the community, as well as understanding of transmission. Awareness of HIV co-infection included here.
Understanding of testing methods based on community interviews in addition to a literature review of systems of testing in place in home country. Most other countries do not conduct routine screening or treatment for latent TB infection (LTBI).
TB treatment including traditional medicine and treatment system in home country.
Physician access, cultural factors affecting access to health care, medical system in home country.
Information regarding experiences of TB care in the U.S., barriers to care including health coverage, language access.
Brief overview of select historical factors that have impacted various aspects of life in the home country, including political and economic issues.
Additional health concerns and common medical conditions in the community.
Abbreviation for short-course of LTBI treatment consisting of combination of rifapentine with isoniazid for weekly treatment for three months (3HP).
Abbreviation for short-course of LTBI treatment consisting of daily rifampin for four months of (4R)
An attenuated (weakened) strain of Mycobacterium bovis. Introduced in 1921, administered primary to newborns in countries with high TB prevalence. It protects against severe forms of TB, such as miliary and meningeal TB, particularly in children. Efficacy in preventing pulmonary TB in adults is variable and generally lower (Lange 2022). The BCG World Atlas provides details of immunization rates for most countries (www.bcgatlas.org, Zwerling 2011). BCG vaccine is not routinely administered in the U.S. BCG vaccination can result in false positivity of tuberculin skin tests.
TB that occurs outside of the lungs. This cCan affect any organ, though commonly affects the lymph nodes, pleura, genitourinary system, bones and joints, gastrointestinal tract, central nervous system, and pericardium (Golden 2005).
Blood test to detect TB infection by measuring the immune response to Mycobacterium tuberculosis antigens. Alternative to the tuberculin skin test. Benefits include no return visit for reading results, no cross-reactivity with the Bacillus Calmette-Guérin (BCG) vaccine, less likely false positive from non-tuberculous mycobacteria.
Antibiotic used in the treatment of LTBI. Can be used in combination with rifapentine for weekly dosing for three months (3HP). Previously was the recommended agent for LTBI treatment as monotherapy for 6 to 9 months. Isoniazid alone is no longer a preferred therapy for LTBI treatment. Most notable side effect is the risk of liver injury.
Individual has been infected with Mycobacterium tuberculosis, but bacteria are inactive. Patient without symptoms and is not contagious. Also known as inactive TB, sleeping TB. About 25% of the global population has been infected with TB (WHO 2023).
See tuberculin skin test. Also known as the tuberculin skin test (TST) or PPD test.
Group of mycobacteria related to the bacteria responsible for TB infection and disease (Mycobacterium tuberculosis). NTM can lead to pulmonary disease which resembles TB disease. Over 150 different species have been identified, though most are due to three types: Mycobacterium avium complex (MAC), Mycobacterium kansasii, and Mycobacterium abscessus. NTM are clinically important as they can lead to false positive tests with BCG and (less commonly) IGRA testing.
See tuberculin skin test. Also known as the tuberculin skin test (TST) or Mantoux test.
– Golden MP, Vikram HR. Extrapulmonary tuberculosis: an overview. Am Fam Physician. 2005 Nov 1;72(9):1761-8. PMID: 16300038.
– Lange C, Aaby P, Behr MA, Donald PR, Kaufmann SHE, Netea MG, Mandalakas AM. 100 years of Mycobacterium bovis bacille Calmette-Guérin. Lancet Infect Dis. 2022 Jan;22(1):e2-e12. doi: 10.1016/S1473-3099(21)00403-5. Epub 2021 Sep 7. PMID: 34506734.
– Public Health Seattle & King County (2024). Tuberculosis in Seattle & King County, 2023 Program Summary. 2023 TB Program Summary (kingcounty.gov)
– World Health Organization. (2023). Global tuberculosis report 2023. World Health Organization. https://iris.who.int/handle/10665/373828
– Zwerling A, Behr MA, Verma A, Brewer TF, Menzies D, Pai M. The BCG World Atlas: a database of global BCG vaccination policies and practices. PLoS Med. 2011 Mar;8(3):e1001012. doi: 10.1371/journal.pmed.1001012. Epub 2011 Mar 22. PMID: 21445325; PMCID: PMC3062527.

In this video, KCPH introduces you to the navigators at the forefront of the TB prevention and treatment work and explore how this innovative program is leading the way for a TB free King County.

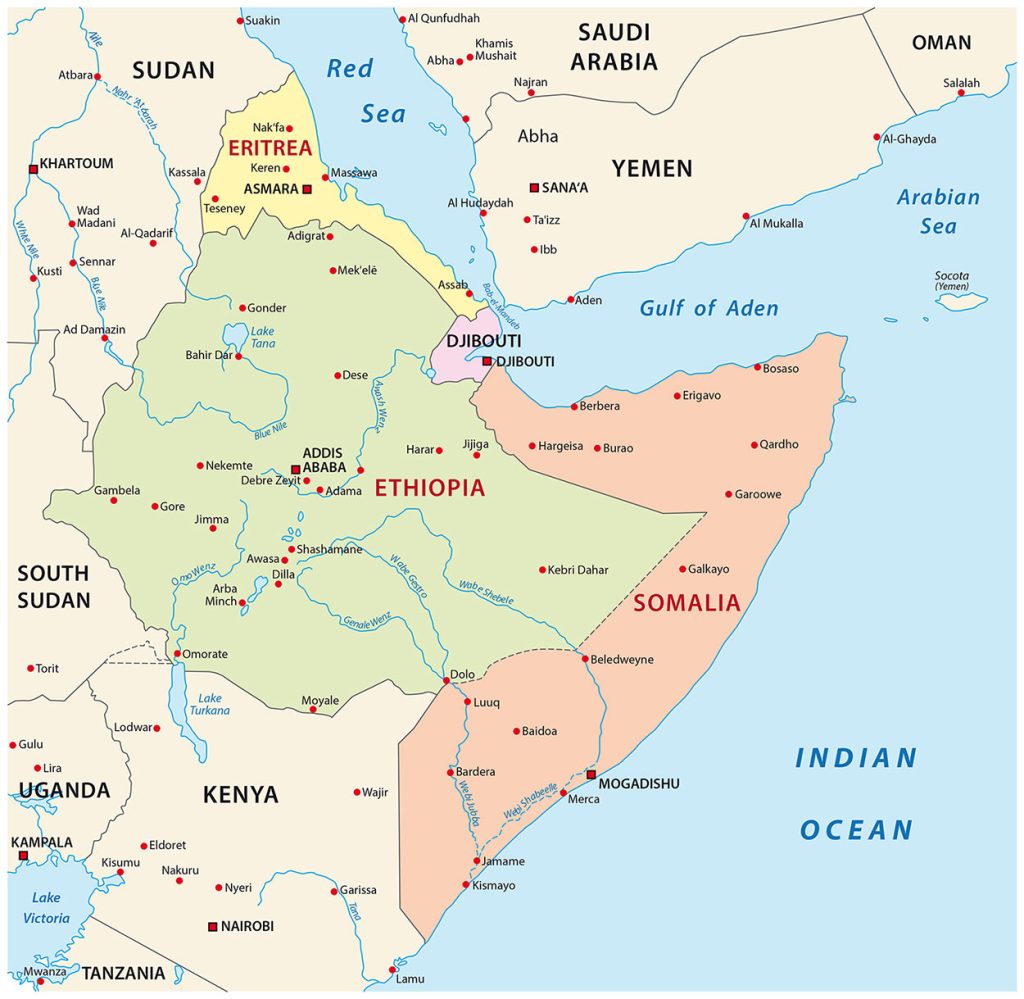
Individuals born in Ethiopia constitute 4.5% of Seattle immigrants and refugees and 7% of tuberculosis (TB) cases in King County, WA as of 2024. Ethiopia has one of the highest HIV/TB burdens in the world. Given this, knowledge of TB disease is common among the Ethiopian community, although knowledge of latent TB is less familiar. TB care for this community must acknowledge values of collectivism, religion, and doctor-patient rapport to build trust.
The following sections are based on interviews with Amharic-speaking Ethiopian community members in King County, Washington and supplemented by data from a literature review. The interviews were conducted by EthnoMed staff in 2025 with English translation as needed. Most respondents spoke fluent English with occasional interpretation in Amharic. One respondent had previously received treatment for active TB disease, one respondent was a physician who had worked at an MDR-TB center in Ethiopia, and the other two had recently attended an EthnoMed educational TB seminar.
2024 TB Statistics in Ethiopia (1)
– Total TB incidence: 186,000
– Total TB incidence (rate per 100,000 per year): 141
– Total TB deaths: 21,800
HIV and TB:
– HIV-positive TB incidence (number): 12,000
– HIV-positive TB incidence (rate per 100,000): 9.3
– Total Population: 132 million
2024 TB Statistics in the USA
Proportion of TB cases in King County, WA among individuals born in Ethiopia: 7%
Ethiopia is home to over 80 diverse languages. Amharic is the government’s official language, but Oromo, Tigrinya, and Somali are also widely spoken (2). Respondents used a few Amharic phrases when referring to TB. The most common phrase employed by both health providers and community members was Samba nekersa (Samba nəqərsa); Samba which translates to lung and nekersa which translates to cancer. The Americanized acronym of TB itself was commented to be frequently used in medical practice. In the community, the terms Ye-sal beshita (Ye-sal bǝššita) and Ye-bərd beshita (Ye-bərd bǝššita) are also used. Ye-sal translates to “cough”, Ye-bard to “chronic cold”, and beshita to “disease”. The four terms were noted to be used interchangeably. One respondent who worked as a physician pointed out the phrase Ye-bərd beshita can be misleading in terms of transmission for the community however.
“…you know, this name, Ye-bərd beshit, okay, associating it with some kind of cold draft air is also a big barrier for the transmission because people, they don’t want to leave their windows and doors open for ventilation. Usually they think it is associated with some cold draft coming through the window or something that is making them sick. So they tend to stay in a poorly ventilated condition…which is very favorable for transmission of TB or any other, you know, aerosol.”
English is the most common foreign language spoken in Ethiopia and many immigrants arrive with a basic command of British English (3). However, one individual still noted that language barriers can create gaps in health care, which has been corroborated by the literature (4).
TB disease was recognized among all respondents and commonly described as a chronic cough, more severe than a common cold. Additional symptoms mentioned included coughing blood, weight loss, weakness, fever, night sweats, loss of appetite, and scrofula. Fewer respondents were aware of extrapulmonary TB, but mentioned TB in the bones or Pott’s disease, abdomen, or liver. There was some association between TB and smoking, but otherwise felt to be indiscriminate. Respondents noted that Ethiopians generally know about TB due to its high prevalence, dedicated TB centers locally, mandatory teaching for HCW, inclusion in school curricula, and increasing presence in the media.
Knowledge of latent TB infection (LTBI) was limited. All respondents did not learn about LTBI until immigrating to the USA and undergoing screening. Upon arrival, it was felt that many Ethiopians are surprised to learn they are positive for TB because they don’t understand the difference between the active and latent forms. It was also not fully understood that LTBI is not contagious, that blood tests do not distinguish between latent or active TB, or that LTBI required treatment to prevent active disease.
Understanding the transmission of TB was more nuanced. While some respondents correctly identified TB spreads via aerosol transmission, one felt that TB is present from childhood and that his intentional weight loss for a surgical procedure is what led to his own TB becoming active. Some correctly identified that the bacteria is asleep and later activated by aging, other diseases, or low immunity. Another mentioned:
“In the villages, there is a belief that you get TB not from other people, but from certain spiritual thing in the sky, some star. In local areas. Particularly the older generations who lack education. Now, it is far better, people are more aware of transmission – mobile everywhere, radio communication, technology everywhere. But still [there is a] wealth problem, some people are poor.”
In terms of diagnosis, most remembered getting a blood test or skin test, though it was not clear if individuals recognized these tests represented latent vs active TB, or how the test worked. Indeed, two respondents were confused why the blood test would still be positive after treatment for LTBI. One respondent noted that chest x-ray and sputum testing were well-recognized to rule out active TB.
Screening and treatment of LTBI in Ethiopia is limited. The physician noted that the burden of TB is so high in Ethiopia that from a public health standpoint, only select individuals like those with HIV undergo screening and treatment for LTBI as described below. Indeed, according to the most recent National Guidelines in 2021, Ethiopia only screens and treats LTBI among TB household contacts ≤15 years old, or patients who: require anti-TNF therapy, dialysis dependent, pre-transplant, living with HIV, living with silicosis. In this case, screening is symptom based, or the use of adjunctive chest x-ray is recommended if available. Standard TB preventative therapy (TPT) in Ethiopia used to be six months of isoniazid, but more recently has changed to 3HP or three months of weekly rifapentine and isoniazid (5).
For active TB, individuals generally are familiar with the process of receiving a chest x-ray and sputum testing. Per the 2021 national guidelines, molecular based testing with PCR (Xpert MTB/RIF) is now also approved for rapid diagnostic confirmation and rifampin resistance testing (5). Respondents commented that people being treated for active TB would go to a hospital and two noted there is a dedicated TB hospital near Addis Ababa (the capital city). The national guidelines for treatment of drug-sensitive TB are to use the global standard of HRZE (rifampin, pyrazinamide, isoniazid, ethambutol) for an intensive, two-month phase followed by four months of HR (rifampin, isoniazid) alone. Of note, BPALM (bedaquiline, pretomanid, linezolid, moxifloxacin) is now also used in Ethiopia for treatment of MDR-TB. One respondent noted there are some local, homeopathic methods of TB treatment among rural communities such as consuming continuous raw eggs or eucalyptus tree ointment.
Ethiopia initiated its National Immunization Program (NIP) for routine childhood immunizations in 1980 which included the Bacillus-Calmette-Guerin (BCG) at birth (6). Despite this, the overall national coverage of BCG between 2000-2019 was only 65.5% (7). As of 2024, 84% of live births in Ethiopia were vaccinated with one dose of BCG (8). The inadequate rates of vaccination have been sourced to issues with health care accessibility in rural or impoverished regions (7).
All respondents were familiar with BCG as a routine childhood vaccination, however, understanding of how the BCG worked was mixed. None of the respondents questioned how people acquire TB despite being vaccinated, and another commented BCG minimized risk of having TB again. One physician commented that in his experience there was also not much detailed awareness that the BCG caused a false positive tuberculin skin test (TST).
Ethiopia has one of the highest TB and HIV coinfection rates globally (9). In fact, one respondent called HIV and TB coinfection, the “new TB.” The current national guidelines in Ethiopia recommend LTBI screening and TB preventative treatment (TPT) only among select, priority populations which includes people living with HIV (PWH) (5). Because TB is so endemic, additional lab or chest x-ray screens are not felt to add value in low-resource settings, so TB is screened by symptoms alone; if asymptomatic, PWH are treated for LTBI and if symptomatic, treated for active TB. In 2024, the CDC reported over 5,606 PWH were diagnosed and treated with TB, and 31,216 PWH received TPT, achieving an 86% completion rate (10).
However, one of the Ethiopian physicians interviewed noted the clinical symptom-based TB screening of PWH has mixed reception by Ethiopian providers. Some providers hesitate to screen based off clinical symptoms alone because TB symptoms may be less overt in PWH due to their impaired immune systems. This can result in delayed treatment and development of antimicrobial resistance:
“Physicians think that we don’t have enough diagnostics to rule out the presence of active TB. Because most HIV patients may not have overt symptoms, there were some circumstances that after isoniazid prophylactic therapy was started, patients developed symptoms and came with what looks like there was [active] TB which was not diagnosed and then was reactivated after [LTBI treatment] just started. So that created more fear like, oh, we don’t have adequate tools to really rule out active TB….”
Generally, stigma still surrounds TB to a significant extent, particularly in Ethiopia more than the U.S. While two respondents felt there was no shame or discrimination to having TB, other respondents felt it was stigmatized because it causes serious disease, which is consistent with the literature. One respondent who had TB disease previously noted that coughing too much in public places may cause discomfort and staring. Another noted people avoid being seen when retrieving TB medicines, or deny knowing anyone with TB. In a recent study of 3463 individuals living in Addis Ababa, one-third of participants reported stigma toward TB, with 20.5% stating TB patients are rejected by the community.
“If some people know that you have TB or tuberculosis, people scared to come to you and to talk with you and to eat with you, they’re scared. So that’s why [affected individuals] feel shame.”
This shame may translate into the initial shock of Ethiopian immigrants who receive a LTBI diagnosis. Providers may combat this stigma by counseling on the non-infectious nature of LTBI and normalizing the commonality of TB diagnosis worldwide.
Despite the high burden of TB in Ethiopia, the TB program only received 2.1% of total health expenditures in 2016/2017. The government only funds 11.7% of TB program funding, while the rest derives from external donor funding or out of pocket patient costs. A lack of a centralized, cohesive financial management system also challenges tracking expenditures to support greater budget advocacy (11).
On the individual level, the cost of TB care represented a catastrophic 21% of a person’s annual household incomes (11). While TB confirmatory lab tests and anti-TB drugs are free or exempt through public health facilities, any other lab tests, hospitalizations, nutrition, and medications for comorbidities are not and must be paid out-of-pocket by the patient. In 2011, Ethiopia introduced a community-based health insurance (CHBI) plan to expand health care coverage to communities in rural settings. This would likewise help cover the costs of non-TB services. However, as of 2019, only 28% of the population reported enrollment in CHBI for reasons which are multifactorial and outside the scope of this document (12). Most importantly, 54% of TB costs are indirect, such as missing work and difficulties in finding transportation, which cause significant disparities for vulnerable, low-income individuals (11).
To improve TB funding, six strategic initiatives were outlined by the Ethiopian government in 2022 including increasing the domestic allocation of government funds to TB programs, coverage of non-medical costs like nutritional supplements, and integration of TB services into CHBI packages.
Some respondents felt their experience with American doctors was overall positive. They left positive feedback toward the TB informational sessions left by EthnoMed teachers on TB. Some themes did emerge as barriers to care in the U.S. however.
One common theme seen in the literature (4) and our interviews was how the U.S. health care system emphasizes screening for preventable or chronic diseases which is unfamiliar to Ethiopians who are accustomed to seeking out medical care only when sick. Specific to TB, respondents did not undergo screening for LTBI until immigrating to the USA. At this juncture, it was felt that many Ethiopians experience surprise and distress from testing positive when they do not understand the difference between latent and active TB. Consequently, one physician highlighted that when first meeting a patient from Ethiopia, building trust may be more important than diagnosing or treating LTBI or other health screenings to improve care retention:
“I think that was one of the tricky things that was happening that public health noticed, was some people’s first interaction with healthcare is after they get a diagnosis for latent TB in other communities, and they don’t have an existing relationship with that provider, and then it’s kind of a traumatizing event. So, then it’s much more difficult, I think, for the provider in that situation to be able to have their recommendations accepted. Yeah, yeah. I think if something goes wrong at some point, then the tendency to label that doctor or that clinic as not good and ruin their reputation is very high. They can label the doctor or the clinic as not doing a good job.”
Furthermore, respondents agreed that while members of the Ethiopian community may be open to LTBI screening, they may be more resistant to LTBI treatment. One community member explained that this is because the TB treatment is not 100% guaranteed by physicians to prevent active TB, so they felt the side effects of preventative treatment were not worth it. This sentiment was further fueled by the inability of the Quantiferon to distinguish treated vs untreated LTBI. Another noted that lack of symptoms is a barrier to receiving LTBI treatment resulting in patients being lost to follow-up or not swallowing the pills.
“We asked the doctor there, are you sure that we can be treated 100%. They said, no, we cannot assure you. Then if you are not assuring me that 100%, then I will come when it will wake up. If it is sleeping, let it sleep! (laughs)”
Culturally, it was explained that physicians in Ethiopia can be more authoritative, sometimes referred to as “next to God”, so individuals may place less value or trust in the less directive and more consultative recommendations of an American physician.
One respondent also expressed concern over the high health care costs in the U.S. despite having insurance, particularly for medication and surgery. Exact health care coverage data for Ethiopian-born U.S. citizens is unavailable, but it is estimated that in Seattle roughly 5.0% of uninsured, non-U.S. citizens are Ethiopian/Amharic speaking compared to 0.3% nationwide (13). Fortunately, within Washington state, health insurance is available for purchase on the marketplace regardless of documentation or immigration status as of January 2024 (13). Regardless, obtaining insurance is confusing and challenging among Ethiopian immigrants unfamiliar with the new healthcare system (4). Connecting patients with a social worker or community navigator may help navigate this gap.
As of 2022, 356,000 individuals in the U.S. are either born in Ethiopia or of Ethiopian heritage. Most have settled in Washington D.C., but other states including California, New York, Minnesota, Texas, and Washington as well.
The first diaspora occurred after the 1974 Ethiopian Revolution when people were fleeing political repression and violence under the authoritarian, Derg regime (14). This period of the Red Terror saw the execution or imprisonment of thousands of political opponents. The second wave of immigration occurred in the 1990s when people fled famine and economic hardship during the transitional period after Derg fell. A more recent diaspora occurred in 2022 when a civil war broke out resulting in the U.S. Department of Homeland Security announcing eligibility to apply for temporary asylum (3).
In a qualitative analysis of Ethiopian immigrants, cultural beliefs important to maintaining health included preserving one’s cultural heritage, family and friend social support, religion, freedom, and respectful health care interactions (15). Many Ethiopians have religious roots in Christianity or Islam and view the church as an important community space for exchanging information (3,4). Some might view illness as punishment from God (15). As a collectivist society, individuals might live in large family groups and make joint health decisions with a spouse or other family member. Translated to TB care, providers might inquire if the patient would like the provider to discuss the diagnosis and treatment with any other family members. Clinics might partner with community navigators like religious leaders to deliver health lectures.
See Ethiopian Cultural Profile for more details.
Obesity and diabetes were identified among the respondents and literature as major comorbidities in the Ethiopian community since living in the U.S. This was attributed to American foods containing more sugar and chemicals, insufficient sleep, and long work hours in sedentary jobs (4). Other respondents were concerned about comorbidities like hypertension, back pain, or vision problems. In contrast, back home, respondents mentioned the main health concerns were poverty and malaria. Within the literature, other comorbidities to consider are mental health concerns or substance use which may not be spoken about openly (4). This has been sourced to the stress of immigration, social isolation, financial stressors, and assimilating to a new culture with unfamiliar customs (4).
1. World Health Organization. Tuberculosis profile: Ethiopia [Internet]. 2026 [cited 2026 Mar 6]. Available from: https://worldhealthorg.shinyapps.io/tb_profiles/?_inputs_&tab=%22tables%22&lan=%22EN%22&iso3=%22ETH%22&entity_type=%22country%22
2. Language data for Ethiopia. CLEAR Global [Internet]. [cited 2026 Mar 6]. Available from: https://clearglobal.org/language-data-for-ethiopia/
3. EBSCO [Internet]. [cited 2026 Mar 13]. Ethiopian immigrants | Social Sciences and Humanities | Research Starters | EBSCO Research. Available from: https://www.ebsco.com
4. Kassa MH, Vaughn LM, Amsalu B, Schnadower Z, Jorga I, Habte A, et al. Community Health Needs Assessment of Ethiopian American Immigrants in Two Nontraditional Migration Cities. J Health Care Poor Underserved. 2025 Aug;36(3):830–54. doi:10.1353/hpu.2025.a967335
5. Ministry of Health – Ethiopia. Guidelines for Clinical and Programmatic Management of TB, TB/HIV, DR-TB and Leprosy in Ethiopia – 7th edition. Addis Ababa, Ethiopia; 2021.
6. Federal Ministry of Health, Addis Ababa, April 2015. ETHIOPIA NATIONAL EXPANDED PROGRAMME ON IMMUNIZATION.
7. Atalell KA, Alemayehu MA, Teshager NW, Belay GM, Alemu TG, Anlay DZ, et al. Mapping BCG vaccination coverage in Ethiopia between 2000 and 2019. BMC Infect Dis. 2022 Jun 23;22:569. doi:10.1186/s12879-022-07547-4 PubMed PMID: 35739462; PubMed Central PMCID: PMC9219134.
8. Immunization Data [Internet]. [cited 2026 Mar 12]. WHO Immunization Data portal – Detail Page. Available from: https://immunizationdata.who.int/global/wiise-detail-page
9. World Health Organization. Global Tuberculosis Report 2025 [Licence: CC BY-NC-SA 3.0 IGO] [Internet]. Geneva; 2025 [cited 2025 Dec 16]. Report No. Available from: https://iris.who.int/server/api/core/bitstreams/e97dd6f4-b567-4396-8680-717bac6869a9/content
10. CDC. Global HIV and TB [Internet]. 2025 [cited 2026 Mar 12]. HIV and TB Overview: Ethiopia. Available from: https://www.cdc.gov/global-hiv-tb/php/where-we-work/ethiopia.html
11. Lang E. Tuberculosis Domestic Resource Mobilization and Sustainability Roadmap for Ethiopia.
12. Ethiopian Public Health Institute, The DHS Program ICF Rockville, Maryland, USA. Ethiopia Mini Demographic and Health Survey 2019: Final Report. 2021.
13. Buettgens M, Ramchandani U. The Health Coverage of Noncitizens in the United States, 2024.
14. EBSCO [Internet]. [cited 2026 Mar 13]. Red Terror in Ethiopia | History | Research Starters | EBSCO Research. Available from: https://www.ebsco.com
15. Chiatti BD. Culture Care Beliefs and Practices of Ethiopian Immigrants. J Transcult Nurs. 2019 Jul 1;30(4):340–9. doi:10.1177/1043659618817589


The devastation wrought by the Khmer Rouge regime led to an international Cambodian diaspora, including resettlement of close to 150,000 people in the United States since 1975. Cambodian refugees started new communities in California, Washington, Massachusetts, and Minnesota (1). These communities have developed to include cultural centers such as Khmer Buddhist temples where refugees and their families could teach the next generation their language and traditions.
Medical literature has shown that Cambodian refugees have high rates of depression and post-traumatic stress disorder (PTSD) (2,3). Ethnographic research also shows evidence of disrupted family dynamics and dependence on substances such as alcohol (3, 4). These problems persist decades after the resettlement of Cambodian refugees in the United States and affect new generations of Cambodian-Americans as well. A lack of culturally responsive mental health treatments is noted in many studies that investigate the continued mental health needs of Cambodian refugees (3, 5, 6).
Culturally responsive mental health treatment is difficult to pursue as it requires dedicated time to understand a community’s perspective on mental health issues and adequate resources to develop and implement an appropriate response. However, this time and resource allocation is clearly needed to address the underrated mental health needs of the Cambodian community. In one study, 97-100% of Cambodian refugees who had seen a doctor for mental health concerns were prescribed a psychotropic medication with limited use of trauma-focused psychotherapy (7). The first-line standard of care for PTSD, which many Cambodian refugees have, is psychotherapy, yet Cambodian refugees’ use of pharmacotherapy is nearly double that of White Americans and 6 times that of other Asian American groups. Furthermore, Cambodian people may be prescribed medications but not adhere to treatment in a way that would enable them to see therapeutic effects. Cambodian cultural navigator Jeniffer Huong reports that during her home visits, “Nobody takes” the medications prescribed, and “only when I have a headache” or other problem acutely come up would somebody reach for a medication (8). She understands that community members are not used to taking a medication daily for ongoing chronic disease.
A target for intervention is community-based programs to improve understanding of mental health disorders and implement long-term, sustainable efforts to improve the mental health of the Cambodian refugee community. One such community-based program was successfully implemented in Lowell, Massachusetts, an area with the second-largest concentration of Cambodian Americans in the United States (9). Their community health center integrated Cambodian staff members to explain health concepts and consulted with Buddhist monks; this health center saw an improvement in depression screening scores over the course of the program. Cambodian Americans in Seattle believe that using Buddhism studies and classes at temple will help connect the second generation to their parents’ experience and grapple with the ongoing mental health needs of refugees and their families (10). Another program that improved mood, the Cambodian Health Promotion Program in Massachusetts, used five health educational sessions to provide culturally tailored health promotion education wherein an American mental health practitioner and a Cambodian community health worker co-lead small group sessions (11).
Piloting a program based on the Cambodian Health Promotion Program would be an achievable and impactful project to improve PTSD and depression in the Cambodian community. The curriculum is available on request, and sessions could be modified to address health topics like trauma and heightened emotions, which was not in the original curriculum. As EthnoMed has a contingent of community health workers already, deploying this curriculum in a community-based setting such as a Buddhist temple or Cambodian gathering space would be an effective strategy to promote mental health in the Seattle Cambodian community.


Emma Lazarus
In search of resources to assist your patients with immigration concerns? Here are some useful links to assist patients and providers.
As a reminder, Harborview Medical Center is a public institution that complies with regulatory policy. These materials may not reflect the most updated institutional policy around immigration enforcement action.

Tuberculosis (TB) is a serious bacterial infection that affects the lungs and can spread to others if left untreated. In many countries, the Bacillus Calmette-Guérin (BCG) vaccine is given to children to protect them from the worst kinds of TB. However, protection wanes over time and people who received the BCG vaccine as children can still get TB later in life. It is important to use the TB blood test instead of the skin test since the skin test can react to the BCG vaccine. (or you can say: It is important to use the TB blood test instead of the skin test since it more accurate).content and videos here.
To ensure that non-English-speaking community members receive accurate information about TB, we have created multilingual public service announcements (PSAs). These short videos provide essential details about the BCG vaccine in multiple languages. Health care providers and community organizations are encouraged to share these PSAs with individuals who may be at risk.

To support providers in addressing rising measles cases, we’ve created a short video PSA available in seven languages commonly spoken in King County and other diverse communities. These videos are designed to be shared with patients and families to increase awareness about measles and the importance of MMR vaccination. Language access includes: English, Arabic, French, Lingala, Somali, Spanish, Swahili, and Ukrainian.
Each video features culturally and linguistically appropriate messaging that addresses common concerns and emphasizes the safety and effectiveness of the vaccine.
Please share these videos with your community!

Tuberculosis (TB) is a serious bacterial infection that affects the lungs and can spread to others if left untreated. Many people are unaware that TB exists in two forms: latent TB infection (LTBI) and active TB disease. Early screening and treatment can prevent the spread of TB and protect community health.
To ensure that non-English-speaking community members receive accurate information about TB, we have created multilingual public service announcements (PSAs). These short videos provide essential details about TB screening, treatment, and prevention in multiple languages. Health care providers and community organizations are encouraged to share these PSAs with individuals who may be at risk.
Each PSA explains;
If you haven’t been screened for TB yet, talk to your primary care doctor or visit a local clinic. If you don’t have a primary care provider, King County Public Health TB program can help you find a place to get tested (HealthPoint, SeaMar, or Neighborcare). Visit the King County Community Health Access program for more assistance.
Taking care of your health starts with knowing your TB status. Together, we can prevent TB and keep our communities healthy!
We offer these PSAs in multiple languages to serve diverse communities. Click below to watch and share:
This project has been generously supported by the following funders:
TB Elimination Alliance (2023-2024 Mini-Grant Program)
Firland Foundation (2024-2025 Community Grant)

This resource was developed by the research team at the University of Washington Family Medicine Residency to assist providers and patients in finding social and support services for pregnant individuals. It includes a list of community organizations and state-funded programs designed to help pregnant patients reach their full potential during the perinatal period and immediately afterward. Created in 2024, this document features the most current information available. However, services and details may change over time, so please visit the individual websites for the latest updates.


“Providing community-based support during pregnancy, birth, and early parenting to nurture strong foundations that last a lifetime.”
Doulas, prenatal and postnatal support, home visiting, lactation support, community education, peer support groups, baby essentials, resource and community events, resource navigation and referrals support. Fill out the online intake form or call 206-866-0729 openarmsps.org

“To create culturally responsive pregnancy and parenting experiences for Black, immigrant, and refugee families.”
Doula, lactation support, support groups, resource coordination, infant/child developmental screening. For doula support, submit intake form. Find out about how to get connected for other resources on their site, globalperinatal.org

A doula referral service serving all population groups.
Visit their website, seattledoulapartners.com

“Nurturing Expressions provides caring, evidence-based healthcare and support for expecting and new parents. We specialize in lactation, chest and breastfeeding, breast pump education and care, and mastectomy and compression garments.”
Services include Breast/Chest feeding resources, lactation resources for all population groups.
nurturingexpressions.com

“Our mission is to support families through the specialty of infant feeding–with the most up-to-date research, warmth, and compassion. We specialize in the diagnosis and treatment of tongue tie and related issues.”
Services for tongue tie, home therapy, feeding help, body work, and advocacy resources for all populations groups. Patients should inquire with their insurance about coverage. Email inquiries here, more information, seattlebfclinic.com

“Our mission is to provide the skills necessary for refugee and immigrant women and their children in Washington state to reach their highest potential.” “We partnered with local community-based organizations, governments, and funders to extend a strong web of resources and deliver them in an equitable, culturally sensitive way.”
‘Best 4 Babies’ and ‘Flourishing under Five’ -Programs for pregnant mothers or mothers with children under, case management, and other resource connections. Serving immigrant and refugee populations from Africa. Call (253) 277-7625, email, or visit motherafrica.org

“Family Ways is a program supporting pregnant persons, parenting families and children up to age five. All services are culturally relevant, participant-centered, and strengths-based. Our Peer Community Specialists represent the communities we currently serve.”
Peer support to connect to resources and classes; assists with connections; can assist with essentials. social work, nutrition, and nursing. Serving all populations, visit the Family Ways King County website.

First Steps King County maternity support services and infant case management. Includes Nurse Family Partnership which provides one on one home visits with specialty nurse through the second year of age. Individualized and personalized to family needs. Assist with resource connection.
Nurse-Family Partnership is a community health program that helps transform the lives of people pregnant with their first child. The program partners families with registered nurses from pregnancy through a child’s second birthday, allowing nurses to deliver the support first-time parents need to have a healthy pregnancy, become knowledgeable and responsible parents, and provide their babies with the best possible start in life. The relationship between parent and nurse provides the foundation for strong families, and lives are forever changed—for the better.
Serving anyone with Medicaid. Referrals can be made using this form or call 206-263-8374, more information on the website.

Refugee Women’s Alliance “promotes inclusion, independence, personal leadership, and strong communities by providing refugee and immigrant women and their families with culturally and linguistically appropriate services”
Provides comprehensive 10 wrap-around social services including but not limited to ESL classes, employment, job training, housing, behavioral health, and legal services. Serving immigrant and refugee communities. Call 206-721-0243 or email, or visit rewa.org

Habla Therapies provides comprehensive and compassionate speech language therapy for children facing a range of challenges. Their expertise spans across English and Spanish evaluations, ensuring that every child feels comfortable and understood during their therapeutic journey.
Service include pediatric dysphagia, infant bottle aversions, difficulty transitioning to solids, sensory feeding challenges/picky eating, childhood apraxia of speech, stuttering, dyslexia, and speech, language, and social-pragmatics delays. Serving all populations, visit the website hablatherapies.com

Consejo is a licensed, award-winning treatment center offering outpatient behavioral health care, trauma-informed care, and supportive transitional housing. Since 1978, Consejo has served children, youth, adults, and elders in King, Pierce, and Thurston-Mason County.
Offering primary healthcare to all populations. Call (206) 461-4880 or more information here, consejocounseling.org

Their mission is: “help clients attain the highest level of self-sufficiency in Western society while maintaining their cultural identities”
Serving Asian Americans and Pacific Islanders and other underserved communities – including immigrants, refugees, and American-born. Schedule an appointment online, call (206) 695-7600 or email. More information here, acrs.org.

“Perinatal PCL is a free, state-funded program providing perinatal mental health consultation, recommendations and referrals for Washington state providers caring for pregnant or postpartum patients.”
Serving all populations. Call 1-877-725-4666 or email, more information on the website.

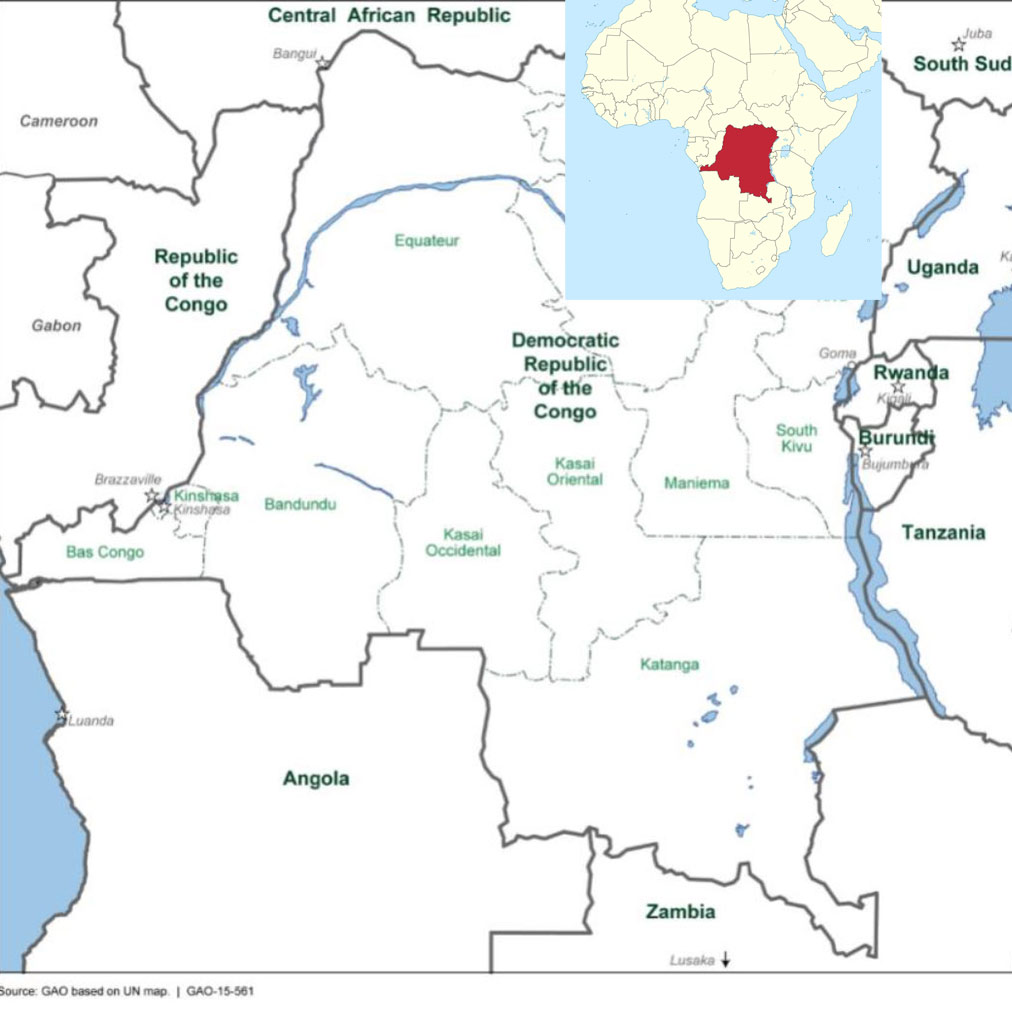
The Democratic Republic of Congo (DRC) has a high incidence of tuberculosis (TB) disease, ranking 8th highest in the world. Individuals may be hesitant to undergo screening due to a history of political instability and autocratic rule resulting in widespread distrust, lack of understanding of the U.S. medical system, and the dual stigma of TB and its associations with human immunodeficiency virus (HIV). There is confusion in the community regarding the diagnosis of latent TB infection (LTBI) and its distinction with TB disease. There is also less awareness of blood testing (e.g. interferon-gamma release assay, Quantiferon) because skin testing has been more prevalent in the DRC, though LTBI screening is not routinely conducted there. Many recent immigrants mentioned TB treatment in the DRC being offered from the same medical clinics where HIV patients are treated, which compounds the stigma of the disease.
The following sections are based on transcripts of interviews with six Congolese community members who were identified by a Congolese community navigator contracted with Public Health – Seattle & King County and through other community contacts. Interviews were conducted either in English or French with a Congolese community navigator providing interpretation. A supplemental literature review was also performed.
2022 WHO statistics of the Democratic Republic of the Congo (DRC) [1]
Total tuberculosis (TB) incidence (number): 314,000
Total TB incidence (rate per 100,000 per year): 318
HIV-positive TB incidence (number): 22,000
HIV-positive TB incidence (rate per 100,000 per year): 22
Total Population (2023): 102 million (www.data.worldbank.org) [2]
French is the official language of the DRC. However, there are four additional recognized national languages: Kikongo, Lingala, Swahili, and Tshiluba.
Most francophones in the DRC know of tuberculosis by the French term “tuberculose”. In Lingala, it is sometimes referred to as “Kosu Kosu ya ntolo ” which means chest cough, or “kosu kosu ya pema”, which refers to chronic cough. In Swahili, tuberculosis is “Kifua Kikuu”.
The BCG Vaccination was introduced to the DRC in 1984. A single dose is administered at birth.
There is an estimated BCG coverage of 73% in 2019 [3] (www.bcgatlas.org).
Some respondents noted a common perception of the BCG vaccination being protective against TB disease, even into adulthood.
Most respondents identified symptoms of TB disease as being chronic. Community members stated that their level of suspicion for TB increased with persistent symptoms, particularly symptoms of cough, fatigue, or weight loss. However, only some respondents understood that TB infection can be latent or inactive. Respondents who were familiar with latent TB infection referred to it as “sleeping” TB. Overall, there is a consensus among respondents that there is a general lack of awareness in the Congolese community regarding the distinction between TB disease and latent TB infection (LTBI).
All respondents understood that TB is contagious and transmitted via coughing/breathing. Some noted that individuals with TB disease are usually isolated from the general public and that it is dangerous to be in close contact with someone diagnosed with TB.
TB is considered to be a serious disease with the potential to be fatal.
Clinicians should recognize the intertwined nature of the HIV-TB co-epidemic, not only in medical clinical terms but also in its social consequences.
Most respondents noted that there is a widespread perception that TB disease occurs in those with HIV infection. A perceived similarity in symptoms like weight loss and fatigue perpetuates the stigma against TB disease and creates a double stigma against TB and HIV/AIDS [4] (Daftary 2012). The interlinked nature of these two illnesses can lead to individuals concealing their TB disease status or preventing them from seeking treatment in an attempt to avoid stigma.
In the DRC, TB and HIV care are funded by Global Fund, and TB disease cases are usually treated in HIV clinics. Directly observed therapy (DOT) is widely practiced for TB disease treatment in the DRC. Patients who are required to go into HIV clinics daily to receive treatment for TB disease often face double stigma. Since most of the general public is aware that HIV requires lifelong treatment, the relatively long treatment period of TB disease (6-9 months) further increases the association between the two diseases.
The DRC ranks eighth among countries with the highest rate of TB/HIV co-infection [5] (https://www.who.int/teams/global-tuberculosis-programme/tb-reports/global-tuberculosis-report-2023).
There is an estimated HIV prevalence of 0.6%, with about 490,000 HIV positive individuals out of a total population of about 95 million. Based on recent WHO data (https://cfs.hivci.org/index.html) globally, both rates of new infections and deaths due to HIV have been decreasing over the past decade [6]. However, about 6.3% of TB cases in 2022 occurred in HIV positive individuals.
People with untreated HIV infection or AIDS are at increased risk of TB disease because HIV weakens the immune system and impairs the body’s ability to fight off TB infection. HIV is the strongest risk factor for progression from TB infection to TB disease. Extrapulmonary and disseminated TB are also more common in HIV infected individuals [7] (Schutz 2010).
Among high drug-resistant countries, DRC is ranked 12th. According to the WHO, the estimate of MDR-TB/XDR-TB at the national level was 2.4% in new patients. One meta-analysis found that HIV infection raises the risk of MDR-TB, with an upward risk trend [8] (Sultana 2021).
Testing and latent infection
In 2021, the DRC National Tuberculosis Control Program (Programme National de Lutte contre la Tuberculose, PNLT) implemented a new national strategy for diagnosing and treating LTBI across the country. Health authorities increased free active screening of TB by organizing campaigns and sending out mobile units with rapid diagnostic testing [9] (WHO 2022). However, most respondents stated that they are not aware of routine testing for TB.
Traditional medicine is still of importance for people in the DRC, with a recent study showing that 79.4% of the studied population have utilized this care system [10] (Mutombo 2022). Some respondents noted that traditional first-line treatment for cough is an herb or leaf that is boiled and then consumed as a drink. If cough and other symptoms persist, individuals will often then seek Western medical treatment.
There is a general consensus that most people trust the treatments recommended by the medical system in the DRC. However, respondents noted that general awareness of information regarding TB screening, diagnosis, and treatment as well as the level of trust in Western medicine depends on place of residence (rural versus urban) and level of education.
TB treatment is free in the DRC with approximately 2,000 centers delivering TB care for 180,000 patients in 2019 [11] (Kaswa 2021). However, out-of-pocket spending is significant even for TB patients, with over half of patients experiencing catastrophic healthcare costs [11] (Kaswa 2021).
There is a recognition that treatment for TB spans over several months, and that it is a treatable disease. Respondents also note that there is a general fear of death or serious illness from TB if untreated.
There are about 18,493 physicians in the DRC, about 1.9 doctors per 10,000 inhabitants. As a comparison, the worldwide density has been 17 physicians per 10,000 inhabitants [12] (https://www.who.int/data/gho/data/themes/topics/health-workforce). However, despite the low rate of human resources, this may not be the primary barrier to care in the DRC. Clinic visitation rates are low, suggesting that other primary barriers to care, including cost, impact care-seeking behavior [13] (Nyakasane 2022).
There are several significant challenges to implementing effective TB screening in the Democratic Republic of Congo (DRC). One major issue is the reliance on traditional medicine, especially in rural and underserved areas. Many people in the DRC consult traditional healers for chronic illnesses while simultaneously using modern medical treatments. This dual approach can lead to complications, including adverse drug interactions, which can undermine the effectiveness of TB treatments. With limited access to health services in certain regions, traditional medicine fills a gap but can delay early TB detection and treatment, exacerbating the spread of the disease.
Additionally, there is a general understanding that TB is an infectious disease requiring isolation from the community and the general public. One respondent noted that in the DRC, those infected with TB were historically placed in isolation facilities which also held individuals with psychiatric disorders and other diseases. While this practice is no longer in use in the current healthcare system in the DRC, many individuals still associate TB diagnosis with forced isolation. Respondents stated that community members would generally keep their distance and avoid those who have been diagnosed with TB. Because of this, many tend to keep their diagnosis concealed from the general community and instead seek support from community leaders. Since Congolese communities are more widely dispersed in the US, it is easier to conceal TB status from the community.
Additionally, the rise of evangelical churches in the country has altered health-seeking behaviors. Christianity is the predominant religion in the DRC, with approximately 95.4% of the general population affiliated with Christian denominations [14] (USCIRF 2020). Respondents note that Congolese Christians rely heavily on prayer when dealing with sickness, and that many turn to pastors for prayer before seeking out treatment from doctors. Pastors are key figures in the community who inspire and command trust. Some individuals now seek religious validation for medical diagnoses, which can delay care for TB and other communicable diseases. Pastors may either affirm or dismiss a diagnosis, causing further delays in accessing appropriate medical care.
These cultural and religious factors, combined with inadequate health infrastructure, make it difficult to implement widespread TB screening programs, particularly in remote or underserved regions of the DRC.
Mpox
An outbreak of Mpox was declared in the DRC in December 2022. More recently, an outbreak with a new variant has occurred in the mining regions of South Kivu and North Kivu province with evidence of human-human transmission [15]. Currently there is evidence of transmission due to sexual contact, non-sexual contact, as well as household and healthcare facility contacts. There is an estimated fatality rate of around 5% in 2024 [15]. There is currently no data on the rate of co-infection with TB.
Malaria
The DRC is the second most malaria-affected country in the world, and accounts for 12.3% of global malaria deaths [16] (https://www.who.int/news-room/fact-sheets/detail/malaria). However, it is difficult to ascertain the prevalence of co-infections due to the lack of available diagnostic tests.
In 2019, there were 61,000 Congolese nationals residing in the U.S. [17] (https://www.migrationpolicy.org/article/sub-saharan-african-immigrants-united-states-2019 ). A total of 11,400 refugees were resettled in the United States in fiscal year (FY) 2021, 43 percent of whom were from the DRC—the largest single country of origin for all refugee settlement that year [17] (https://www.migrationpolicy.org/article/sub-saharan-african-immigrants-united-states-2019). Noncitizen immigrants and asylum seekers are significantly more likely to be uninsured compared to U.S. citizens. Many Congolese asylum seekers have more limited access to private coverage, and they face eligibility restrictions for federally funded coverage. Those who are eligible for coverage also face a range of enrollment barriers including language and literacy challenges as well as complex eligibility rules. Therefore, even when LTBI screening is conducted by public health campaigns, many individuals have limited options for treatment of LTBI.
Before and upon arrival to the U.S., refugees are screened for TB. Screening with chest x-ray alone occurs for refugees abroad, prior to entering the U.S. LTBI screening consists of skin testing (such as TST or Mantoux) or IGRA (such as Quantiferon) as part of the domestic refugee screening. Repetition of testing, particularly with different modalities, can act as a source of confusion (e.g. a negative test result in their home country or refugee camp, and a positive test in the US). Consequently, when individuals are diagnosed with LTBI after they were previously told they were negative for TB (such as with a chest x-ray), this can decrease confidence in their diagnosis and the medical system.
The DRC had been colonized in two phases: by King Leopold II of Belgium from 1885 to 1908 and by the Belgium state from 1908 to 1960. These reigns were characterized by the exploitation of precious natural resources as well as widespread human rights abuses, with longstanding effects on the country and its people.
Between the 1920s and 1950s, Western colonial governments implemented extensive medical campaigns in sub-saharan Africa, including present day DRC, aimed at managing tropical diseases such as sleeping sickness, syphilis, leprosy, yaws, and malaria [18] (Lowes and Montero 2021). During this period, millions of people were subjected to medical examinations and forced to receive injections or medications with unreliable efficacy and serious side effects.
The legacy of these campaigns can be seen in present day distrust in Western medicine, which can lead to a lower utilization of healthcare and avoidance of preventative or screening measures.
The DRC has the world’s largest cobalt reserves and the seventh-largest copper reserve. Today, cobalt is used in the manufacture of nearly all lithium-ion batteries. By 2025, demand for cobalt is expected to reach 222,000 tons, triple that of 2010. The expansion of industrial-scale cobalt and copper mines has led to the forced evictions of entire communities without just compensation or sufficient resettlement, as well as serious labor and human rights abuses.
In the DRC, cobalt is being extracted by “artisanal” miners—freelance workers who do dangerous labor for the equivalent of a few dollars a day. Miners work in grueling conditions, with many women and children digging for cobalt with their bare hands or rudimentary tools. Few safety precautions are available, few have access to masks to prevent breathing in toxic dust from cobalt [19]. https://www.amnesty.org/en/wp-content/uploads/2021/05/AFR6231832016ENGLISH.pdf
Political conflict has been a frequent occurrence since the country’s independence from Belgium in 1960. Since the 1990s, there has been increased civil tension and conflict brought on by attempts to overthrow the autocratic military regime that had reigned for several decades. The Rwandan genocide in 1994 also led to an influx of around 1 million refugees to the DRC [20]. (https://www.cfr.org/global-conflict-tracker/conflict/violence-democratic-republic-congo)
The First Congo War occurred in 1996-1997 with major spillovers into Sudan and Uganda which ended the autocratic regime of Mobutu Sese Seko. The Second Congo War extended from 1998 to 2003, though intermittent conflicts continue.
Since January 2013, UNHCR reports that more than 400,000 Congolese nationals have sought refuge outside DRC. Uganda, Rwanda, Tanzania, Burundi, and Angola are the primary host countries providing asylum to Congolese refugees. Most Congolese refugees have resided in refugee camps and urban centers where basic services are limited or unavailable.
Several respondents mentioned nutrition as a prominent concern in the Congolese community, particularly among those who recently arrived in the U.S.
The traditional Congolese diet consists of freshly grown, unprocessed foods. In the U.S., access to local, traditional ingredients is limited. Fast food or processed foods are cheaper and more readily available. The effects of these processed foods are seen in the rise in non-communicable diseases such as diabetes and heart disease in the population.
Conan Doyle, A. 2023. The Crime of the Congo
Hochschild, A. 1998. King Leopold’s Ghost: A Story of Greed, Terror and Heroism in Colonial Africa.
Kara, S. 2023. Cobalt Red: How the Blood of the Congo Powers Our Lives.
Predergast, J., et al.2018. Congo Stories: Battling Five Centuries of Exploitation and Greed
Reid, S. 2023. The Lumumba Plot: The Inside Story of a CIA Assassination
Reybrouck, D. 2015. Confo: The Epic History of a People
Stearns, J. 2012. Dancing in the Glory of Monsters: The Collapse of the Congo and the Great War of Africa
This project has been generously supported by the following funders:
TB Elimination Alliance (2023-2024 Mini-Grant Program)
Firland Foundation (2024-2025 Community Grant)
1. https://worldhealthorg.shinyapps.io/tb_profiles/?_inputs_&lan=%22EN%22 Accessed 22 August 2024.
2. https://data.worldbank.org/indicator/SP.POP.TOTL?end=2023&locations=CD&start=1960&view=chart Accessed 9th September 2024.
3. www.bcgatlas.org Accessed 22 August 2024
4. Daftary A. 2012. HIV and tuberculosis: the construction and management of double stigma. Social science & medicine, 74(10), 1512-1519.
5. World Health Organization. Global Tuberculosis Report. Geneva, Switzerland: WHO, 2023 https://www.who.int/teams/global-tuberculosis-programme/tb-reports/global-tuberculosis-report-2023
6. World Health Organization. Democratic Republic of the Congo, HIV Country Profile 2023. https://cfs.hivci.org/index.html
7. Schutz C, Meintjes G, Almajid F, Wilkinson RJ, Pozniak A. 2010. Clinical management of tuberculosis and HIV-1 co-infection.
European Respiratory Journal, 36 (6) 1460-1481. https://doi.org/10.1183/09031936.00110210
8. Sultana ZZ, Hoque FU, Beyene J, Akhlak-Ul-Islam M, Khan MHR, Ahmed S, Hawlader DH, Hossain A. HIV infection and multidrug resistant tuberculosis: a systematic review and meta-analysis. BMC Infect Dis. 2021 Jan 11;21(1):51. doi: 10.1186/s12879-020-05749-2. Erratum in: BMC Infect Dis. 2021 Jan 20;21(1):86. PMID: 33430786; PMCID: PMC7802168.
9.https://www.afro.who.int/fr/countries/democratic-republic-of-congo/news/la-rdc-mise-sur-les-campagnes-de-depistage-actif-gratuit-des-cas-au-sein-de-la-population-pour Accessed September 9th 2024.
10. Mutombo CS, Bakari SA, Ntabaza VN, Nachtergael A, Lumbu JBS, et al. 2022. Perceptions and use of traditional African medicine in Lubumbashi, Haut-Katanga province (DR Congo): A cross-sectional study. PLOS ONE 17(10): e0276325. https://doi.org/10.1371/journal.pone.0276325
11. Kaswa M, Minga G, Nkiere N, Mingiedi B, Eloko G, Nguhiu P, Garcia Baena I. 2021. The economic burden of TB-affected households in DR Congo. The International Journal of Tuberculosis and Lung Disease 25, no. 11: 923-932. doi: 10.5588/ijtld.21.0182. PMID: 34686235; PMCID: PMC8544924.
12. The National Health Workforce Accounts database, World Health Organization, Geneva https://www.who.int/data/gho/data/themes/topics/health-workforce).
13. Nyakasane R, Karume G, McCann K, Shepard DS, Agarwal Harding PS, Roberts LA. 2022. World Bank Consortium: The Big Questions in Forced Displacement and Health. Washington, D.C.: World Bank Group.http://documents.worldbank.org/curated/en/099001106212246276/P1669090e0c4010b0adfa050973837275a
14.United States Commission on International Religious Freedom Annual Report. 2020.
15. World Health Organization. Disease Outbreak News. Mpox: Democratic Republic of the Congo. 15 June 2024. www.who.int/emergencies/disease-outbreak-news/item/2024-DON522
16. World Health Organization. Malaria Fact Sheet. WHO, 2023 https://www.who.int/news-room/fact-sheets/detail/malaria
17. Lorenzi J and Batalova J. 2022. Sub-Saharan African Immigrants in the United States. https://www.migrationpolicy.org/article/sub-saharan-african-immigrants-united-states-2019 Accessed 22 August 2024.
18. Lowes S, and Montero E. 2021. The legacy of colonial medicine in Central Africa. American Economic Review 111, no. 4: 1284-1314.
19. Amnesty International. (2016). THIS IS WHAT WE DIE FOR. In HUMAN RIGHTS ABUSES IN THE DEMOCRATIC REPUBLIC OF THE CONGO POWER THE GLOBAL TRADE IN COBALT (Report INDEX: AFR 62/3183/2016). Amnesty International Ltd. https://www.amnesty.org/en/wp-content/uploads/2021/05/AFR6231832016ENGLISH.pdf
20. Center for Preventive Action. 2024. Conflict in the Democratic Republic of Congo. Conflict in the Democratic Republic of Congo | Global Conflict Tracker (cfr.org) Accessed 22 August 2024.

This booklet in Somali and English uses simple illustrations and basic definitions to describe male and female reproductive anatomy (PDF in sidebar). This booklet originated with requests from the Somali community and the health care providers who serve them for Somali-language education materials on human reproductive anatomy.
The objective in creating this booklet is to support culturally competent medical care for the Somali community and to empower the Somali community in the process. This book is intended for use by health care providers and health educators with their Somali patients or clients. This booklet was created by clinical and public health staff and reviewed by both Somali and non- Somali physicians, as well as a Somali religious leader. According to Islam, discussing human reproductive anatomy is allowed as long as it is for educational purposes (Quran Chapter, 2 verse 223).
This booklet was produced by WellShare International with funding from the Minnesota Department of Health Family Planning Special Project.